Vein Valves or Outflow Become Abnormal
Damaged valves, previous clot-related changes, or other venous problems can impair normal return of blood from the lower leg.

 EN
Slow-Healing Leg Wounds
A leg ulcer is an open sore that is not healing normally. Some ulcers develop when chronic venous pressure damages the skin around the lower leg and ankle, but arterial disease, diabetes or neuropathy, pressure, injury, infection, and other conditions can produce wounds that need a different approach.
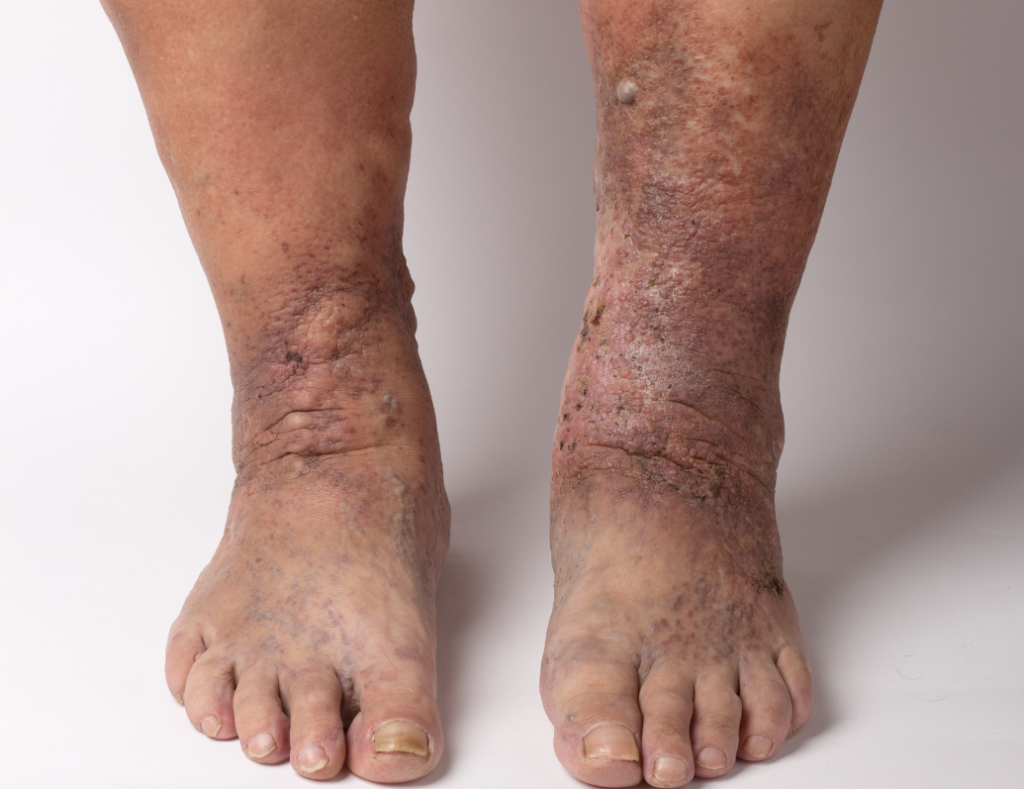
Early-stage clues can appear before an open sore
Venous ultrasound when the pattern fits

Recognize the Wound Pattern
A leg ulcer is a break in the skin that remains open or repeatedly reopens instead of following the expected healing process. The appearance alone cannot tell you the cause, but the wound location and the surrounding leg changes provide important clues.
Where is the wound?
Venous ulcers often develop in the lower leg or around the ankle. Ulcers on the toes, foot, heel, or pressure points can follow a different pattern.
What was happening before the skin opened?
Persistent ankle swelling, brown or reddish skin, itching, firmness, or recurrent irritation can accompany chronic venous disease before ulceration.
How is the wound changing?
A sore that remains open, enlarges, drains, becomes more painful, or returns after healing deserves medical assessment rather than continued self-treatment.
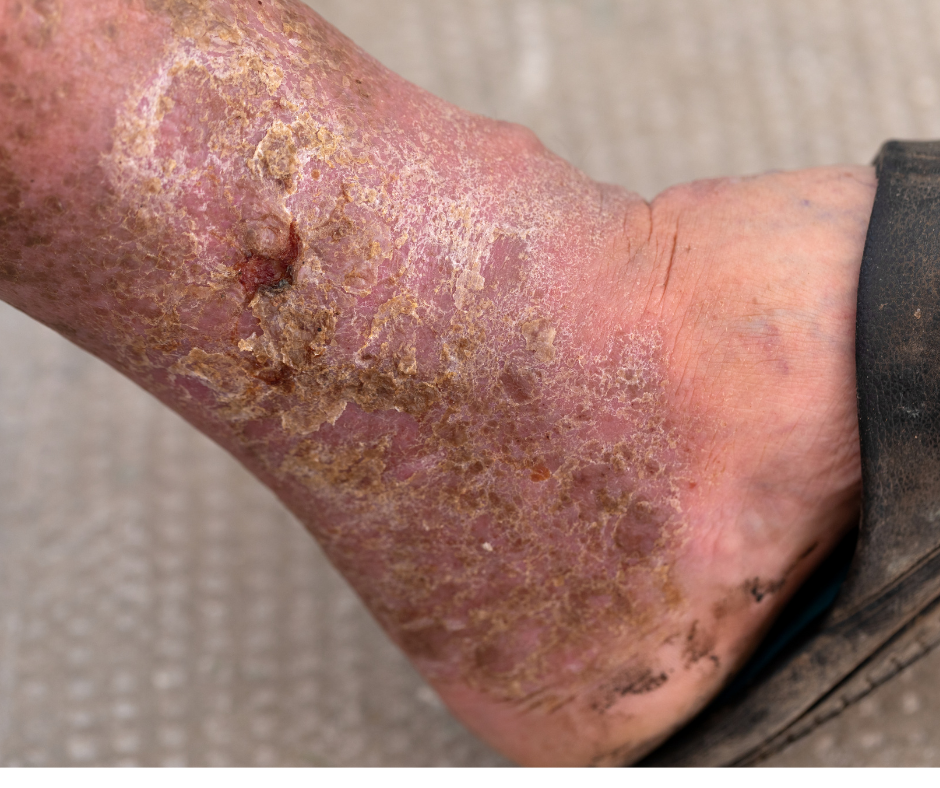
One Possible Venous Pathway
This sequence applies only when a wound is related to chronic venous disease. Venous ulcers develop from sustained pressure and tissue change over time, not simply because a visible vein is present.
Damaged valves, previous clot-related changes, or other venous problems can impair normal return of blood from the lower leg.
Blood and fluid can remain under higher pressure in the lower leg, especially during prolonged time upright.
Persistent edema and inflammation can change skin color, texture, and resilience around the ankle and lower leg.
Long-standing venous hypertension can leave the skin firm, irritated, fragile, or slower to recover from a small injury.
A shallow wound may develop and remain open unless both the wound itself and the contributing circulation problem are addressed.
Look Beyond the Open Sore
The wound itself is only one part of the picture. A venous cause becomes more plausible when the ulcer location and the surrounding lower-leg changes follow a recognizable chronic venous pattern.
Venous ulcers commonly appear in the lower leg, often near the ankle rather than at a toe or pressure point on the foot.
Edema around the wound can be another sign of elevated venous pressure, particularly when it becomes worse while upright.
Long-term venous disease can produce pigmentation and inflammatory skin changes around the lower leg before or alongside ulceration.
Venous dermatitis and tissue fibrosis can make the skin dry, irritated, thickened, or firm around the affected area.
Venous ulcers can occur in legs that have a longer history of heaviness, aching, pressure, or fatigue that worsens during time upright.

Venous ulcers may be moist or draining, and recurrence after healing can signal that the underlying circulation problem still needs attention.
A wound's appearance cannot confirm that it is venous. Arterial disease, diabetes, neuropathy, pressure injury, infection, inflammatory disease, and other causes can overlap with or mimic a venous ulcer.
Explore Related Symptoms
Possible Causes
Leg ulcers are a wound pattern, not one disease. The cause determines which tests, wound-care measures, circulation treatments, and specialists are appropriate.
Venous reflux, obstruction, or damage after a prior clot can create sustained lower-leg pressure that contributes to swelling, skin damage, and venous ulceration.
Reduced arterial blood flow can cause painful wounds on the toes, feet, or lower leg and changes whether compression or other wound treatment is safe.
Loss of sensation, pressure injury, impaired circulation, and slower healing can contribute to diabetic or neuropathic ulcers, often on the foot.
Prolonged pressure over the heel or other bony areas can damage tissue, particularly in people who spend long periods sitting or lying in one position.
A cut, scrape, blister, burn, or other injury may fail to heal when circulation, swelling, infection, or repeated friction interferes with recovery.
Vasculitis, inflammatory disease, malignancy, and other less common disorders can produce chronic wounds that need a different diagnostic pathway.
Compare the Wound Patterns
Location, wound depth, surrounding skin, sensation, pulses, and medical history help clinicians decide which circulation tests or wound specialists may be needed.
Possible Venous Pattern
Often shallow and irregular in the gaiter area near the ankle, with swelling, drainage, pigmentation, dermatitis, or hardened surrounding skin.
Arterial Circulation Pattern
Often appears on the toes, foot, or outer ankle and may be deeper, drier, and more painful, especially when the foot is cool or pulses are reduced.
Neuropathic / Pressure Pattern
Frequently develops at a pressure point on the foot and may be surrounded by callus, especially when reduced sensation makes repetitive trauma harder to notice.
Know When to Act
A wound that is slow to heal, keeps reopening, or is changing in appearance deserves assessment. The goal is to identify infection, circulation problems, pressure, diabetes-related issues, and other causes before the wound becomes harder to manage.
A vein evaluation is most relevant when the ulcer sits in a venous pattern and the surrounding leg also shows swelling, pigmentation, varicose veins, or other signs of chronic venous disease.
The Wound Is Not Closing or Keeps Reopening
A persistent lower-leg sore should not be treated as a routine scrape once normal healing has stalled or the same area repeatedly breaks down.
The Ulcer Is Near the Ankle With Swelling or Skin Changes
This combination can fit chronic venous disease, especially when there is a history of varicose veins, heaviness, or long-standing ankle swelling.
Pain, Warmth, Drainage, Odor or Fever Is Increasing
Worsening pain, surrounding warmth or swelling, cloudy or foul drainage, fever, or chills can signal infection and needs prompt medical attention.
The Foot Is Cold, Pale, Blue, Numb or Painful at Rest
These can be signs of reduced arterial blood flow. Arterial disease requires a different evaluation and can change whether compression is safe.
You Have Diabetes, Neuropathy or an Unclear Wound Cause
Reduced sensation and mixed circulation problems can make wounds more complex. Foot or pressure-point ulcers may need diabetic, podiatric, wound-care, or arterial expertise.
Find the Cause Before Treating the Vein
Texas Vein Experts evaluates whether chronic venous disease is contributing to the ulcer. The visit does not replace wound care, arterial testing, diabetic foot care, or another specialist when those are needed.
Discuss when the sore started, whether it has healed and reopened, previous wounds, swelling, varicose veins, blood clots, diabetes, mobility, and current wound care.
Look at the ulcer location, surrounding skin, swelling, visible veins, temperature, tenderness, and other circulation clues that help separate venous from non-venous patterns.
Ultrasound can map reflux, obstruction, and vein anatomy. It does not diagnose diabetic, neuropathic, dermatologic, or arterial ulcer causes; those may require separate testing.
If venous reflux is confirmed, discuss whether vein treatment may support the broader ulcer plan. If another cause is more likely, the appropriate wound, arterial, diabetic, or other medical pathway comes first.
Treat the Diagnosed Venous Problem
For an active or healed venous ulcer, the wound itself still needs appropriate wound care. If duplex ultrasound confirms superficial venous reflux, treating the abnormal vein may be recommended to reduce the venous pressure contributing to the problem and to help lower recurrence risk.
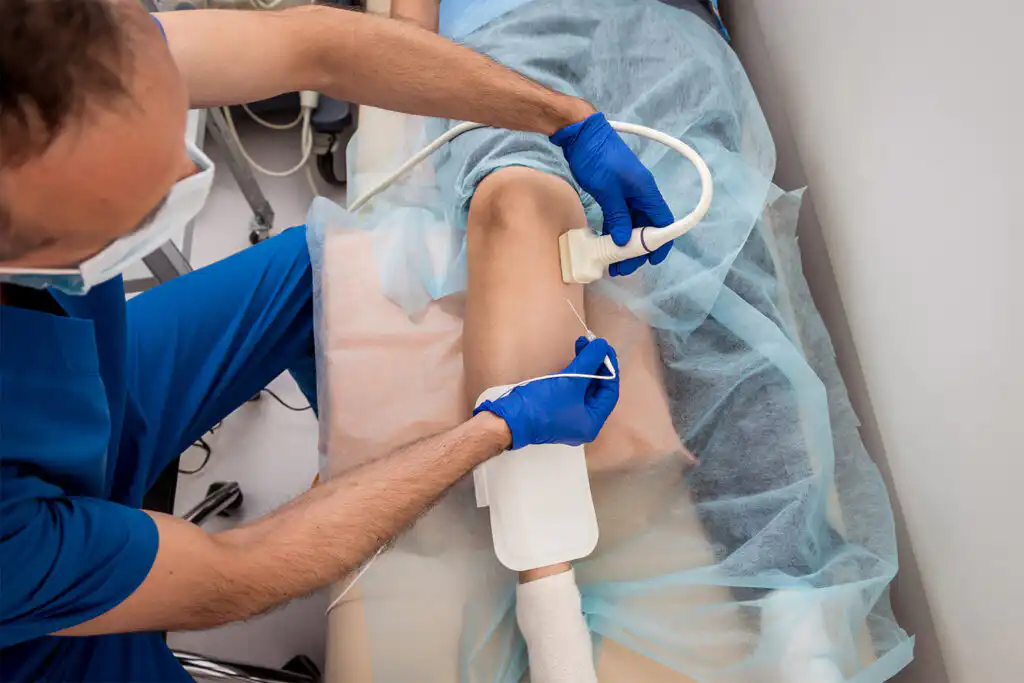
Thermal Catheter Treatment
RFA may be used to close an eligible refluxing source vein when ultrasound shows that superficial venous reflux is contributing to chronic lower-leg venous hypertension.
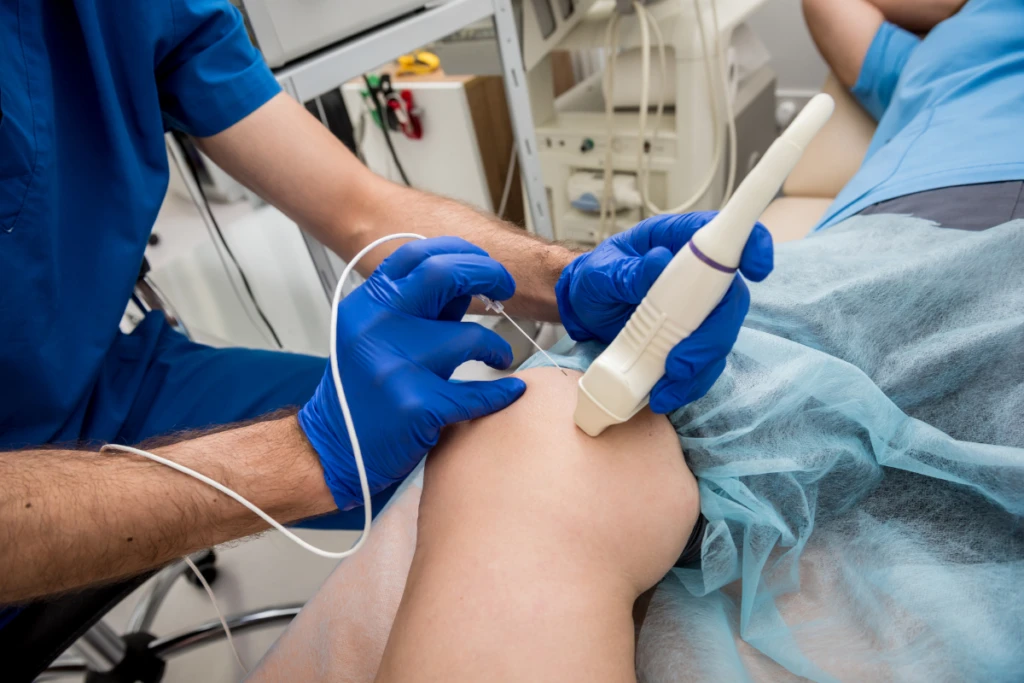
Prescription Microfoam
Varithena may be considered for selected refluxing superficial veins or tortuous varicose pathways when that anatomy is part of the diagnosed venous problem.
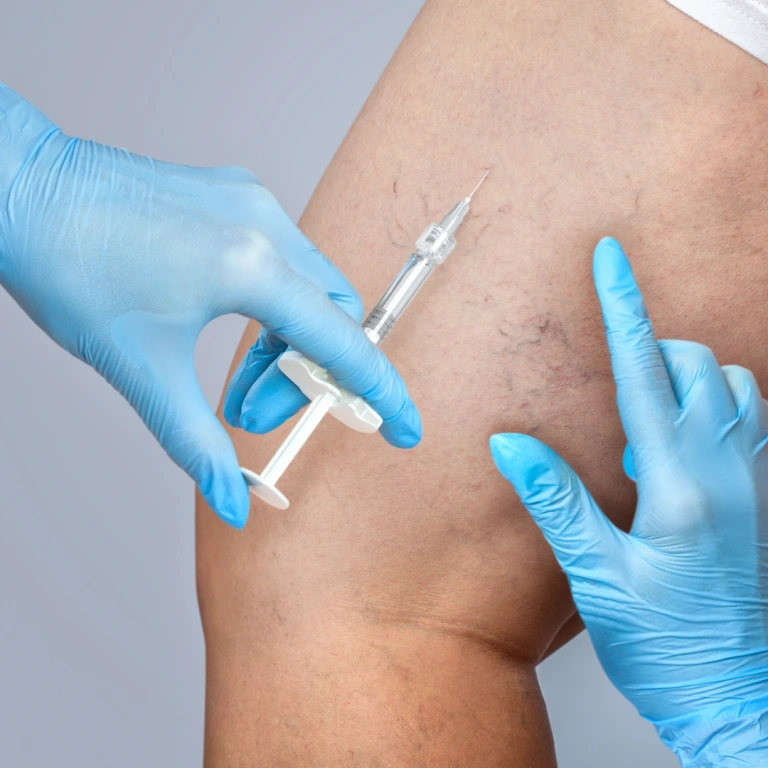
Targeted Injection Treatment
Compounded sclerotherapy can treat selected smaller varicose tributaries or superficial veins when they remain clinically important after the main reflux source has been evaluated.
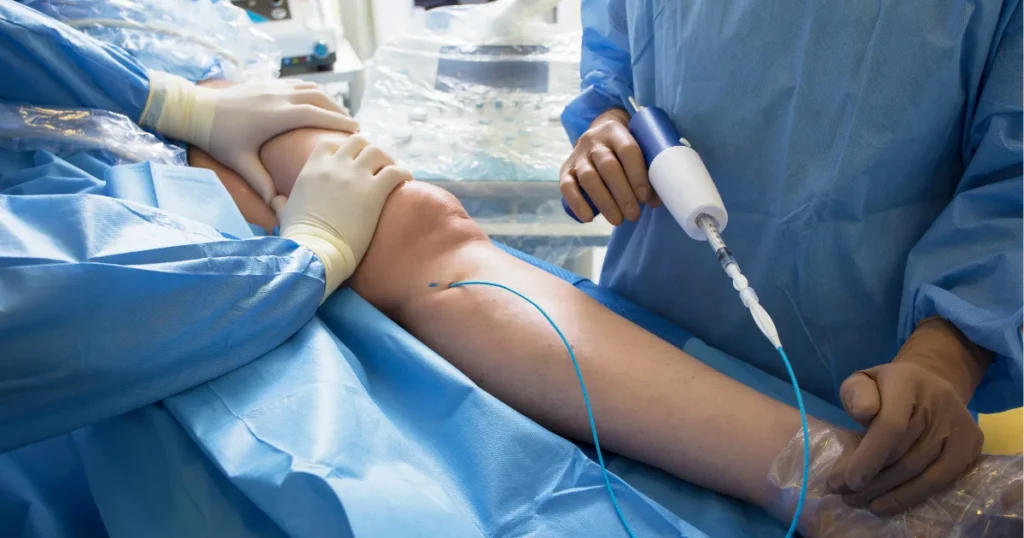
Nonthermal Medical Adhesive
VenaSeal may be an option for an eligible refluxing source vein when the target anatomy and medical history support adhesive closure rather than a thermal technique.
Vein treatment treats confirmed venous reflux, not the ulcer surface itself. Wound dressings, infection management, compression when safe and prescribed, diabetes care, or other specialist treatment may continue alongside or before a venous procedure.
If Venous Reflux Is Confirmed
The goal of a vein procedure is to correct a diagnosed refluxing vein that may be contributing to venous hypertension. It does not guarantee ulcer closure, and wound care usually remains an important part of the plan.
01
Confirm the Refluxing Target
The physician reviews the ultrasound map, the ulcer pattern, and the vein selected for treatment before the procedure begins.
Protect the Wound and Prepare the Treatment Area
Positioning and skin preparation are planned around the current wound, dressings, and the access or injection site required for the vein procedure.
Treat the Confirmed Venous Source
The selected procedure closes the abnormal vein or tributary identified as part of the venous problem; it does not debride or dress the ulcer.
02
Continue the Wound-Care Plan
Dressings, compression when medically appropriate, infection treatment, glucose management, and other wound-specific instructions continue as directed by the clinicians managing the ulcer.
Watch Healing Trends, Not a Fixed Timeline
Ulcer healing varies with wound size, duration, arterial circulation, diabetes, mobility, infection, and other factors. No single vein procedure can promise a specific healing date.
Follow the Vein and the Wound
Follow-up can confirm the treated vein response and determine whether additional venous care, wound care, or another specialist is needed.
Insurance & Medical Necessity
A leg ulcer alone does not determine coverage. Insurance decisions usually depend on the diagnosed venous condition, clinical documentation, duplex findings, medical necessity, the recommended procedure, and the requirements of the individual plan.
Document the Ulcer and Venous Symptoms
Record wound history, swelling, skin changes, previous ulcers, varicose veins, and the effect on daily activity.
Confirm Venous Disease When Indicated
If the pattern suggests a venous cause, duplex ultrasound can document reflux, obstruction, and the anatomy relevant to a treatment recommendation.
Review the Plan's Criteria
The team checks benefits, prior authorization, referral rules, conservative-care requirements, and other insurer-specific criteria that apply to the proposed vein treatment.
Explain the Approved Next Step
Before a venous procedure is scheduled, the team can review the known approval pathway and estimated patient responsibility.
Why Texas Vein Experts?
We do not label every leg ulcer as venous
The wound location, surrounding skin, arterial clues, diabetes history, sensation, swelling, and other findings determine whether vein testing is appropriate.
Onsite duplex can map venous reflux when the pattern fits
Ultrasound helps identify abnormal superficial flow and the vein anatomy that matters if venous disease is contributing to the ulcer.
The physician team includes wound-care experience
Dr. Haider Burney's hospital and wound-care background adds relevant clinical perspective, while all four TVE physicians evaluate and treat venous disease across their regions.
Four minimally invasive vein options are available when appropriate
RFA, Varithena, compounded sclerotherapy, and VenaSeal can serve different roles after the reflux pattern and treatment target are defined.
Your Texas Vein Care Team
Texas Vein Experts physicians evaluate venous disease across DFW, Houston, and San Antonio. Dr. Haider Burney also brings a hospital and wound-care background to the team.

MD, RVT

PA-C, MMS

MPAS, PA-C

FNP-C, FNP-BC

FNP-BC

ANP-C



Common Questions
Clear answers to common patient questions about possible causes, when to get checked, vein evaluation, and treatment options.
A leg ulcer is an open sore that remains slow to heal or repeatedly reopens. It can occur because of venous disease, reduced arterial blood flow, diabetes or neuropathy, pressure, injury, inflammatory disease, or other causes. The wound type has to be identified before treatment is chosen.
Before an ulcer opens, the lower leg may show persistent swelling, brown or reddish discoloration, itching, scaling, inflammation, firmness, or fragile skin. A small break can then become a shallow slow-healing sore, often near the ankle. Those findings are suggestive, not diagnostic.
Venous ulcers commonly develop in the gaiter area of the lower leg, especially around the ankle. Wounds on the toes, sole, heel, or other pressure points may suggest arterial, diabetic, neuropathic, or pressure-related causes instead.
No. Venous disease is an important cause of chronic lower-leg ulcers, but arterial disease, diabetes, neuropathy, pressure injury, trauma, infection, inflammatory conditions, and mixed causes are also possible. A vein clinic should not assume an open sore is venous from appearance alone.
Venous ulcers are often shallow, irregular, and located near the ankle with swelling or skin pigmentation. Arterial ulcers more often affect the toes or foot and may be deeper, drier, and associated with a cool, pale or blue foot, weak pulses, or pain at rest. Mixed disease can occur, so testing matters.
Diabetic or neuropathic ulcers often develop at pressure points on the foot and may occur with numbness, reduced sensation, callus, or repetitive trauma that the patient does not feel normally. Diabetes can also coexist with arterial or venous disease, making a full circulation assessment important.
Increasing pain, warmth, swelling, spreading redness, cloudy or foul-smelling drainage, fever, or chills can suggest infection. These symptoms need prompt medical attention. Antibiotics are used when infection is present, not simply because a wound is open.
A wound that is not closing, keeps reopening, enlarges, drains, becomes more painful, or develops surrounding skin changes should be medically assessed. Clinical guidelines also treat a lower-leg skin break that has not healed within about two weeks as a reason to seek vascular evaluation.
Ultrasound does not diagnose the ulcer type by itself. When a venous cause is suspected, duplex ultrasound can evaluate reflux, obstruction, valve function, and vein anatomy. Arterial disease, diabetic neuropathy, infection, and other wound causes require different assessment.
Arterial circulation should be considered before strong compression is used for a leg ulcer. Significant peripheral artery disease can make compression unsafe or require a modified approach. The appropriate arterial test and compression level should be determined by a qualified clinician.
When superficial venous reflux is confirmed, treating the abnormal vein can be part of evidence-based care for a venous ulcer and may support healing or reduce recurrence risk. The ulcer still needs appropriate wound care, and outcomes depend on many factors beyond the vein procedure.
No. A vein procedure treats the diagnosed venous circulation problem. Wound cleaning, dressings, infection management, compression when safe, diabetes control, off-loading, skin care, and other wound-specific measures may still be necessary.
Yes. Venous ulcers can recur, especially if chronic venous hypertension and swelling continue. Long-term prevention may include treatment of confirmed venous reflux, appropriate compression, mobility, skin care, weight management, and follow-up based on the patient's overall circulation.
Texas Vein Experts offers Radiofrequency Ablation, Varithena, compounded sclerotherapy, and VenaSeal. The appropriate option depends on the reflux source, vein anatomy, wound context, medical history, and duplex findings. Not every ulcer patient needs or qualifies for a vein procedure.
Coverage depends on the diagnosed venous condition, medical necessity, documentation, duplex findings, treatment recommendation, authorization rules, and the individual plan. Wound-care services and vein procedures may have separate coverage requirements.
 English English
 Spanish






